What Are the Guidelines for Treating Type 1 Diabetes in Children?
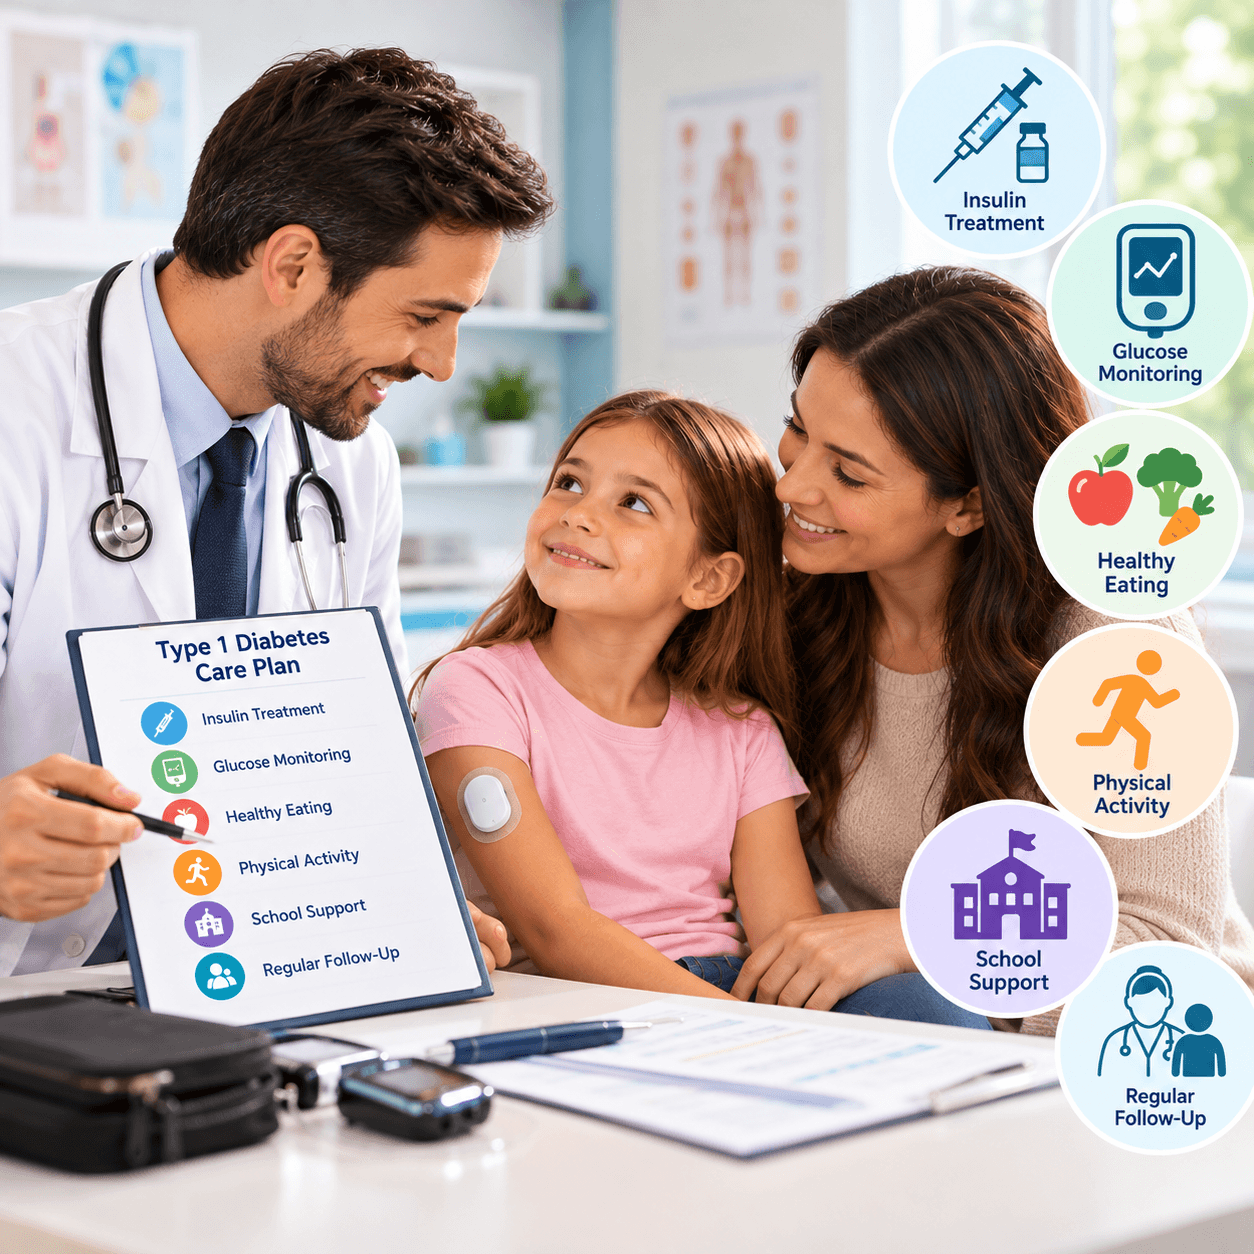
Treating type 1 diabetes in children involves more than simply keeping blood sugar within a certain range. Children need daily insulin, regular glucose monitoring, healthy nutrition, physical activity, and a clear plan for managing low blood sugar, illness, and ketones.
Current guidelines also support using diabetes technology early. Continuous glucose monitoring (CGM) can be offered from diagnosis or as soon as possible, and automated insulin delivery (AID) systems are recommended as an option for children who can use them safely with caregiver support.
The exact treatment plan will look different for every child. Age, growth, activity level, eating habits, glucose patterns, family preferences, and access to diabetes technology can all affect how type 1 diabetes is managed.
Here are the main guidelines parents and caregivers should know.
What Is the Recommended Treatment for Type 1 Diabetes in Children?
Insulin is the main and essential treatment for type 1 diabetes in children. Because the pancreas produces little or no insulin, the body needs insulin from an outside source to regulate blood glucose and prevent serious complications.
Children may receive insulin through:
- Multiple daily insulin injections
- An insulin pump
- An automated insulin delivery system
A child’s insulin needs are not fixed. Doses can change with meals, physical activity, illness, growth, puberty, and the temporary “honeymoon” phase that sometimes occurs after diagnosis.
For this reason, insulin doses should be individualized by the child’s diabetes care team rather than based on general dosing advice.
Why Is Insulin Necessary for Type 1 Diabetes?
Insulin helps glucose move from the bloodstream into cells, where it can be used for energy.
In type 1 diabetes, the immune system damages the insulin-producing beta cells in the pancreas. As insulin production decreases, glucose builds up in the blood.
Without enough insulin, the body also begins breaking down fat for energy. This produces substances called ketones. If ketones accumulate to dangerous levels, a serious condition called diabetic ketoacidosis (DKA) can develop.
This is why insulin should not simply be stopped when a child is sick or eating less. Parents should follow the child’s individualized sick-day plan and contact the diabetes care team when they are unsure about insulin dosing.
How Should Insulin Be Given to Children With Type 1 Diabetes?
Most children need an insulin regimen that provides both background insulin and insulin for meals and glucose corrections.
One common approach is a basal-bolus insulin regimen.
Basal insulin provides background insulin throughout the day and night. Bolus insulin is given around meals or to correct high glucose levels.
An insulin pump can provide these needs using rapid-acting insulin delivered throughout the day. Newer automated insulin delivery systems can also adjust some insulin delivery automatically based on CGM readings.
The best insulin method depends on the child’s:
- Age
- Insulin requirements
- Glucose patterns
- Ability to use diabetes technology
- Family preferences
- Daily routine
- Access to devices and supplies
Children and caregivers should receive ongoing education about insulin administration, dose adjustment, injection or infusion sites, and what to do when glucose levels are outside the child’s target range.
Should Children With Type 1 Diabetes Use a CGM?
Continuous glucose monitoring should be offered to children with diabetes at diagnosis or as soon as possible when it can be used safely.
A CGM is a small device that measures glucose throughout the day and night. Instead of providing only a single glucose reading, it can show whether glucose is rising, falling, or staying relatively stable.
This information can make it easier to identify:
- Low glucose
- High glucose
- Overnight glucose patterns
- Changes after meals
- Changes during exercise
- Glucose trends that may require treatment adjustments
Parents and children still need access to a blood glucose meter. Finger-stick testing may be necessary when a CGM is unavailable, when readings do not match symptoms, or when the device is not working correctly.
Are Insulin Pumps and Automated Insulin Delivery Recommended for Children?
Automated insulin delivery systems are recommended as an option for children and adolescents with type 1 diabetes who can use them safely, either independently or with caregiver support.
An AID system typically combines three components:
- A continuous glucose monitor
- An insulin pump
- An algorithm that uses glucose information to adjust insulin delivery
These systems are sometimes referred to as hybrid closed-loop systems.
AID technology can help improve time spent within the target glucose range while reducing some of the day-to-day work involved in insulin adjustment.
However, technology should fit the child rather than the other way around. Age, comfort with devices, family preferences, cost, availability, and the ability to troubleshoot the system should all be considered.
Children and caregivers also need appropriate training before and during use.
What A1C Level Is Recommended for Children With Type 1 Diabetes?
An A1C below 7% (53 mmol/mol) is an appropriate goal for most children and adolescents with diabetes, according to current ADA guidance.
A1C provides an estimate of average glucose over the previous several months. It helps the diabetes team understand how well the overall treatment plan is working.
However, there is no single perfect target for every child.
A less stringent goal may sometimes be appropriate for children who have severe or recurrent hypoglycemia, difficulty recognizing low blood sugar, limited access to diabetes technology, or other medical or personal circumstances.
In selected children, a lower A1C goal may be appropriate if it can be reached safely without significant hypoglycemia, excessive treatment burden, or negative effects on well-being.
CGM information is also becoming increasingly important. The diabetes team may review:
- Time in range
- Time below range
- Time above range
- Average glucose
- Overnight patterns
- Frequency of hypoglycemia
These measurements provide information that A1C alone cannot show.
How Often Should a Child’s Blood Sugar Be Checked?
Children with type 1 diabetes need glucose monitoring multiple times throughout the day, preferably with CGM when available and appropriate.
If CGM is not being used, blood glucose may need to be checked several times each day.
Monitoring is particularly important:
- Before meals and snacks
- Around physical activity
- At bedtime
- When symptoms of hypoglycemia occur
- When symptoms of hyperglycemia occur
- During illness
- When ketones are suspected
- After treating low blood sugar
The goal is not to produce a “perfect” glucose number every time.
Glucose naturally changes throughout the day. Food, insulin, physical activity, illness, stress, sleep, hormones, and growth can all affect it.
Instead, glucose readings help families and healthcare professionals identify patterns and make safer treatment decisions.
What Should Children With Type 1 Diabetes Eat?
Children with type 1 diabetes generally need the same nutritious, balanced diet recommended for other children, rather than a highly restrictive “diabetic diet.”
Nutrition should support normal growth, development, energy, and a healthy relationship with food.
A balanced eating pattern may include:
- Vegetables
- Whole fruits
- Whole grains
- Beans and legumes
- Lean sources of protein
- Nuts and seeds when age-appropriate
- Dairy products or suitable alternatives
- Healthy fats
- Water as the main beverage
Foods and drinks high in added sugars and highly processed carbohydrates should generally be limited, just as they should be for children without diabetes.
Do Children With Type 1 Diabetes Need to Avoid Sugar?
No. Having type 1 diabetes does not mean a child can never eat sugar or carbohydrates.
What matters is understanding how carbohydrate-containing foods affect glucose and how insulin should be matched to those foods.
Many families learn carbohydrate counting, which involves estimating the amount of carbohydrate in a meal or snack and using the child’s prescribed insulin-to-carbohydrate ratio to determine mealtime insulin.
Parents should avoid making food feel frightening or turning every meal into a discussion about “good” and “bad” foods.
A registered dietitian with experience in pediatric diabetes can help families develop an eating pattern that works with the child’s nutritional needs, culture, preferences, insulin regimen, and normal family life.
How Should Low Blood Sugar Be Treated in Children?
Hypoglycemia, or low blood sugar, should be recognized and treated quickly.
A glucose level of 70 mg/dL (3.9 mmol/L) or below is generally considered the alert level for hypoglycemia.
Possible symptoms include:
- Shaking
- Sweating
- Hunger
- Dizziness
- Irritability
- Weakness
- Difficulty concentrating
- Confusion
- Sleepiness
Mild or moderate hypoglycemia is generally treated with a fast-acting source of glucose, followed by another glucose check after about 15 minutes.
The exact amount of carbohydrate needed can vary, especially in younger children and children using automated insulin delivery. Parents should follow the treatment amount recommended by their child’s diabetes team.
Children should have fast-acting glucose available at home, school, during sports, and when traveling.
When Is Glucagon Needed?
Glucagon is used to treat severe hypoglycemia when a child cannot safely consume carbohydrate by mouth.
Parents, teachers, babysitters, relatives, coaches, and other regular caregivers should know where the child’s glucagon is stored and how to use it.
If a child is unconscious, having a seizure, or cannot swallow safely, do not try to give food or drink by mouth.
Follow the child’s emergency plan, administer glucagon as instructed, and seek emergency medical assistance.
When Should Children With Type 1 Diabetes Be Tested for Ketones?
Ketone testing is particularly important during illness or when a child has significant hyperglycemia.
Ketones can develop when the body does not have enough insulin. Rising ketone levels can be an early warning sign of DKA.
Children with type 1 diabetes should have access to ketone testing supplies, and parents should receive clear instructions about when to use them.
Ketones may need to be checked when:
- The child is sick
- Glucose remains unusually high
- The child is vomiting
- The child has abdominal pain
- There are symptoms suggesting DKA
Parents should follow the ketone thresholds and treatment instructions provided by their child’s diabetes team.
What Are the Warning Signs of Diabetic Ketoacidosis?
DKA is a serious medical emergency caused by severe insulin deficiency and the buildup of ketones.
Possible warning signs include:
- High or rapidly rising glucose
- Elevated ketones
- Excessive thirst
- Frequent urination
- Nausea
- Vomiting
- Abdominal pain
- Dehydration
- Rapid or deep breathing
- Fruity-smelling breath
- Severe tiredness
- Drowsiness
- Confusion or reduced consciousness
DKA can develop quickly in children.
A child with suspected DKA needs urgent medical assessment. Parents should not wait for every symptom to appear before getting help.
How Should Type 1 Diabetes Be Managed When a Child Is Sick?
Children with type 1 diabetes need closer glucose and ketone monitoring during illness.
Illness can raise glucose and increase insulin requirements. At the same time, vomiting or poor appetite can make diabetes management more complicated.
Every family should have written sick-day rules from the child’s diabetes team.
These instructions should explain:
- How often to monitor glucose
- When to test ketones
- How to manage insulin
- What fluids to offer
- How to manage reduced food intake
- When additional insulin may be needed
- When to contact the diabetes team
- When to seek emergency medical care
One particularly important point is that insulin should not simply be stopped because a child is eating less.
Insulin needs may change during illness, but children with type 1 diabetes still need insulin. Follow the child’s individualized sick-day instructions.
Can Children With Type 1 Diabetes Exercise?
Yes. Children with type 1 diabetes should generally be encouraged to exercise and participate in sports.
Physical activity supports cardiovascular health, bone health, strength, emotional well-being, and overall health.
Exercise can also affect glucose in different ways. Some activities lower glucose, while intense exercise can sometimes temporarily raise it.
Children and parents should learn how to:
- Check glucose around exercise
- Use CGM trend information
- Carry fast-acting carbohydrate
- Recognize exercise-related hypoglycemia
- Adjust food or insulin when recommended
- Monitor for delayed hypoglycemia after activity
- Know when high glucose and ketones make exercise unsafe
Diabetes should not automatically prevent a child from joining sports, physical education, or other age-appropriate activities.
How Should Type 1 Diabetes Be Managed at School?
Children with type 1 diabetes need a clear diabetes management plan at school and should be supported in using their prescribed diabetes technology.
Teachers, school nurses, coaches, and other appropriate staff should know how to recognize and respond to hypoglycemia and other diabetes-related problems.
A school diabetes plan may include instructions for:
- Glucose monitoring
- CGM use
- Insulin administration
- Meals and snacks
- Physical activity
- Treating hypoglycemia
- Using glucagon
- Checking ketones
- Managing hyperglycemia
- Contacting parents
- Responding to emergencies
A child should also have appropriate access to diabetes supplies and fast-acting glucose.
As children become older, they can gradually take more responsibility for diabetes care. However, responsibility should be transferred according to the child’s maturity and abilities rather than age alone.
Does Mental Health Matter in Type 1 Diabetes Treatment?
Yes. Emotional and psychological support is an important part of pediatric diabetes care.
Type 1 diabetes requires attention every day. Children may become frustrated with glucose checks, devices, food decisions, insulin doses, or simply feeling different from their friends.
Parents can experience stress and worry as well.
The diabetes care team should pay attention to concerns such as:
- Diabetes distress
- Anxiety
- Depression
- Fear of hypoglycemia
- Family conflict around diabetes
- Disordered eating behaviors
- Treatment burnout
Parents can also help by treating glucose readings as information rather than grades.
A high glucose reading does not mean the child has “failed,” and it does not necessarily mean the parent has done something wrong. The number helps identify what may need attention next.
What Follow-Up Care Do Children With Type 1 Diabetes Need?
Children with type 1 diabetes need regular follow-up with a pediatric diabetes care team.
Treatment needs change as children grow, enter puberty, become more independent, change activity levels, and adopt new diabetes technology.
Follow-up care can include:
- Reviewing glucose and CGM patterns
- Checking A1C
- Adjusting insulin
- Reviewing nutrition and growth
- Checking blood pressure
- Reviewing injection or infusion sites
- Discussing physical activity
- Screening for associated autoimmune conditions
- Reviewing mental and emotional health
- Updating school and sick-day plans
- Screening for diabetes-related complications when appropriate for age and diabetes duration
Type 1 diabetes is also associated with conditions such as autoimmune thyroid disease and celiac disease, so appropriate screening is part of pediatric diabetes care.
What Are the Main Treatment Guidelines at a Glance?
The treatment plan should always be individualized, but the major recommendations can be summarized this way:
| Area of care | General guideline |
|---|---|
| Insulin | Required every day |
| Insulin delivery | Multiple daily injections, pump, or AID system |
| CGM | Offer at diagnosis or as soon as possible when appropriate |
| AID | Offer when the child/caregiver can use it safely |
| A1C | Below 7% for most children, individualized as needed |
| Glucose monitoring | Multiple times daily or continuously with CGM |
| Nutrition | Balanced diet with carbohydrate-management education |
| Hypoglycemia | Recognize and treat promptly; keep fast-acting glucose available |
| Glucagon | Keep available for severe hypoglycemia |
| Ketones | Test during illness or significant hyperglycemia as directed |
| Exercise | Encourage with appropriate glucose and insulin planning |
| School | Have an individualized diabetes management and emergency plan |
| Education | Continue for the child and caregivers as needs change |
These are general guideline principles. A child’s insulin doses, glucose targets, ketone thresholds, and emergency instructions should come from their pediatric diabetes team.
What Are Common Mistakes to Avoid When Treating Type 1 Diabetes in Children?
One of the biggest mistakes is treating type 1 diabetes as if it can be controlled through diet alone. Children with type 1 diabetes need insulin.
Other mistakes to avoid include:
- Missing insulin doses
- Stopping insulin during illness without medical guidance
- Ignoring persistent high glucose or ketones
- Not carrying fast-acting glucose
- Not keeping glucagon available
- Making major insulin changes without appropriate guidance
- Relying on CGM without having backup glucose-monitoring supplies
- Restricting normal childhood activities unnecessarily
- Expecting perfect glucose readings
- Giving a young child too much responsibility too soon
Diabetes management is about identifying patterns and making safe adjustments over time, not achieving a perfect number every hour of every day.
Key Takeaway
The main guidelines for treating type 1 diabetes in children include daily insulin, frequent glucose monitoring, appropriate nutrition, regular physical activity, and clear plans for hypoglycemia, ketones, illness, and emergencies.
Current guidelines also support early use of CGM and automated insulin delivery when these technologies are appropriate and can be used safely.
Treatment should grow with the child. Insulin needs, glucose patterns, independence, food habits, physical activity, and emotional needs can all change over time.
With appropriate treatment, education, technology, and support, children with type 1 diabetes can participate in school, sports, travel, family activities, and everyday childhood.
Frequently Asked Questions
What is the first-line treatment for type 1 diabetes in children?
Insulin is the essential treatment for type 1 diabetes in children. It can be given through multiple daily injections, an insulin pump, or an automated insulin delivery system.
What is the recommended A1C for a child with type 1 diabetes?
An A1C below 7% (53 mmol/mol) is appropriate for most children and adolescents with diabetes, although the target should be individualized.
Should children with type 1 diabetes use a CGM?
Current guidelines recommend offering CGM at diagnosis or as soon as possible when the child and caregivers can use it safely.
Can a child with type 1 diabetes eat sugar?
Yes. Children with type 1 diabetes do not need to completely avoid sugar or carbohydrates. The important part is understanding carbohydrate intake and matching insulin appropriately.
Can children with type 1 diabetes play sports?
Yes. Children with type 1 diabetes can participate in most sports and physical activities with appropriate glucose monitoring, carbohydrate availability, and insulin planning.
What should parents do if their child has ketones?
Follow the child’s individualized ketone and sick-day plan. Elevated ketones, especially with vomiting, abdominal pain, dehydration, deep breathing, or drowsiness, can indicate DKA and require urgent medical attention.
Can insulin be stopped when a child with type 1 diabetes is sick?
Insulin should not simply be stopped during illness. Insulin requirements may change, so parents should follow the child’s sick-day instructions and contact the diabetes care team when needed.
Is type 1 diabetes curable in children?
There is currently no routine cure for type 1 diabetes. Treatment focuses on replacing insulin and managing glucose while supporting normal growth, development, and quality of life.